
Back Pain: Symptoms, Causes and When to Get Help
Key Takeaways
- Most back pain is "non-specific", meaning there is not always one single structure, scan finding or injury that fully explains the pain.
- Staying active and avoiding prolonged bed rest is usually more helpful than complete rest for most mechanical back pain.
- Pain does not always mean damage. Stress, poor sleep, reduced strength and nervous system sensitivity all affect how intense pain feels.
- Red flag symptoms such as loss of bladder or bowel control, numbness around the saddle area, or severe or progressive leg weakness need urgent medical attention.
- Back pain that has not improved after four to six weeks, keeps returning, or is affecting work, sleep or training deserves an assessment.
What is Back Pain?
In many cases, back pain relates to irritation, strain or overload of muscles, joints, discs or nerves in the spine. Pain is not always caused by one single structure, though. A proper assessment looks at your symptoms, movement, strength, lifestyle, work demands and activity levels to understand what may be contributing to the problem.
Clinicians usually classify back pain by the area affected, and each region has its own patterns. Lumbar pain refers to the lower back, the most common form because the lumbar spine takes the greatest load in sitting, bending, lifting and training, and it has its own dedicated guide to lower back pain.


Thoracic pain refers to the mid and upper back between the base of the neck and the bottom of the ribcage, covered in our guide to upper back pain. Cervical pain refers to the neck, which behaves differently enough to have its own guide to neck pain. This page covers back pain as a whole: how it works, the types, the warning signs, and how treatment fits together.
Back pain is also classified by how long it has been present. Acute back pain is recent and short-term. Sub-acute pain has lasted six to twelve weeks and may need a more structured plan. Chronic or persistent pain means symptoms have lasted around three months or more. Where you are in this timeline guides treatment, exercise selection and expectations.
The key point runs through this whole page: most back pain is not caused by one simple fault in the spine. Pain usually comes from a combination of irritated tissue, movement habits, reduced strength, lifestyle load and nervous system sensitivity, which is why good assessment looks at the whole picture rather than one painful structure.
What Anatomy Is Involved in Back Pain?
Your spine is made of vertebrae stacked on top of each other, with intervertebral discs between them acting as shock absorbers. Ligaments hold the vertebrae together, while muscles and tendons provide movement, control and support. The spinal cord runs through the spinal canal, with nerves exiting at each level to supply the trunk, pelvis, legs and feet.
Each disc has a tougher outer ring and a softer centre. When people talk about a “slipped disc”, they usually mean a disc bulge or herniation, where the inner part of the disc pushes outwards and may irritate a nearby nerve. The term is misleading, because discs do not slip out of place.
Facet joints sit at the back of each spinal segment and guide movement. The sacroiliac joints connect the base of the spine to the pelvis. Muscles including the erector spinae, multifidus, glutes, hip flexors and deep abdominals all influence how the back moves and tolerates load.
Pain can come from any of these structures, and in many cases no single tissue explains the whole problem. Back pain typically develops from a combination of load, stiffness, weakness, sensitivity, work demands and recovery factors.
Main Types of Back Pain
Lower Back Pain
(Lumbar Pain)
The most frequent form, often involving muscle strain, joint irritation, or a disc problem. Lower back pain is common enough, and specific enough, that we cover it fully in our dedicated guide to lower back pain.
Upper and Mid-Back Pain (Thoracic Pain)

Nerve Pain and Sciatica
Disc‑Related Pain
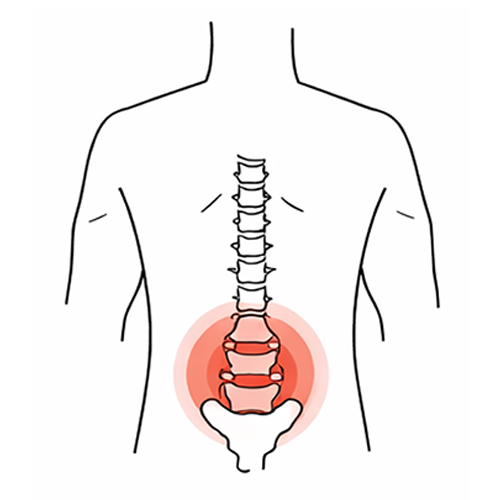
Pain from disc bulges or degeneration affecting nearby nerves, sometimes with pins and needles or numbness.
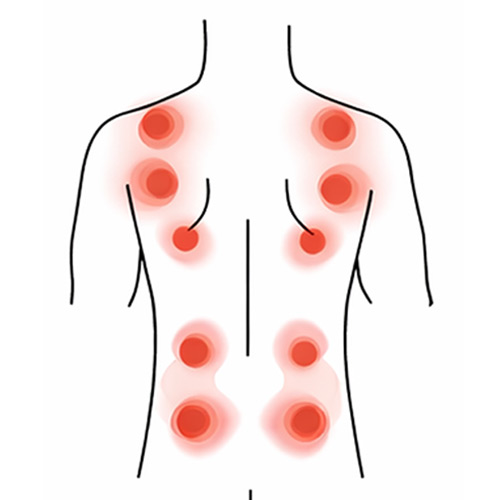
Arthritis and Age‑Related Changes
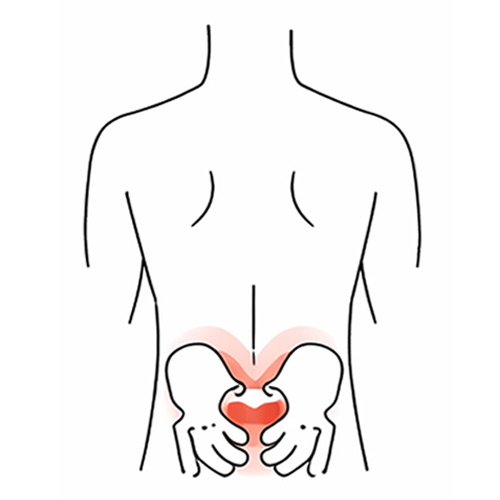
Sacroiliac Joint (SIJ) Pain
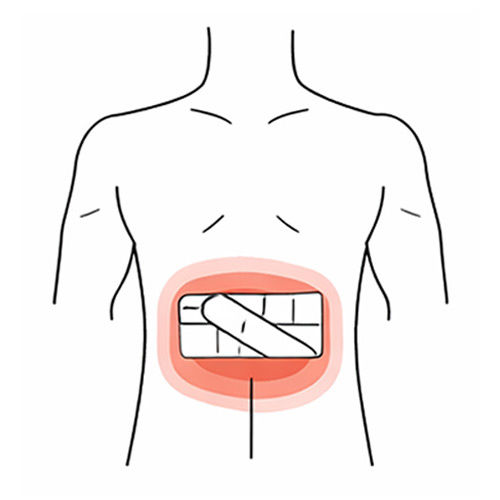
Post‑Operative or Post‑Injury Pain
Common Causes and Contributing Factors
Back pain can have several possible causes and contributors. In many cases, symptoms come from a combination of tissue sensitivity, movement habits, strength, lifestyle load, work demands and recovery factors rather than one single fault in the spine.
Muscle or Ligament Strain
Muscle or ligament strain can happen when the muscles and soft tissues around the spine are overloaded. This may follow lifting, twisting, sudden movement, sport, training or doing more activity than your body is currently prepared for.
Disc Irritation, Bulge or Herniation
A spinal disc can become irritated or bulge towards a nearby nerve root. This may contribute to lower back pain, leg pain, pins and needles or sciatica-like symptoms. However, disc changes can also appear on scans in people without pain, so imaging findings must always be matched with symptoms and clinical assessment. Pain can travel down the leg when the sciatic nerve is irritated. See our guide to sciatica treatment in London.
Facet Joint Irritation
The small joints at the back of the spine can become stiff, sensitive or overloaded, particularly with prolonged standing, repeated arching, or sudden increases in activity.
Degenerative or Age-Related
Changes Spinal osteoarthritis and disc degeneration are common with age. They do not always cause pain, but they can contribute to stiffness and reduced tolerance of certain positions.
Spinal Stenosis
Narrowing around the spinal canal or nerve pathways, more common in older adults. It can cause leg pain, heaviness or cramping when walking, typically easing with sitting or bending forward.
Sacroiliac Joint Pain
Pain from the joint where the spine meets the pelvis, felt deep in one side of the lower back or top of the buttock, and sometimes linked to pregnancy, injury or changes in loading.
Post-Operative or Post-Injury Pain
Pain persisting after trauma, surgery or a long period of reduced activity, where graded rehabilitation rebuilds strength, mobility and movement tolerance.
Less Common but More Serious Causes
Rarely, back pain comes from fractures, infections, inflammatory conditions or cancer, which is why a physiotherapist screens for red flags at every first assessment.
Why Does Back Pain Happen?
There is often a difference between the moment back pain starts and the real reason it developed. You might feel pain after bending down, lifting a bag, twisting awkwardly or getting out of bed, but the underlying issue may have been building for weeks or months.
For many London office workers, the pattern is familiar: long hours sitting at a desk, commuting, training inconsistently, sleeping poorly, then suddenly feeling back pain during a simple movement. Over time, reduced strength, stiff hips, limited thoracic mobility, deconditioning and repeated sitting can reduce your back’s tolerance to load.
Back pain can also be affected by stress. High stress can increase muscle tension, change breathing patterns, reduce sleep quality and make the nervous system more sensitive. This can make pain feel stronger even when there is no serious structural damage.
Poor sleep can also make pain harder to manage because it reduces recovery and increases sensitivity. Smoking, low physical activity, sudden spikes in training, obesity, poor recovery and long periods of sitting may also contribute.
This is why effective back pain management is rarely about one painful area alone. A good assessment looks at the whole picture: your spine, hips, strength, mobility, work setup, training load, recovery, sleep, stress and confidence with movement.
Symptoms and What They Mean
- A dull, persistent ache across the back, often worse after prolonged sitting or standing
- Stiffness first thing in the morning that eases with gentle movement
- Sharp or stabbing pain when bending, twisting, lifting or standing from a chair
- Pain travelling into one or both buttocks or down the leg, which may suggest nerve irritation or sciatica
- Muscle spasm, tightness or guarding on one side of the spine
- Difficulty straightening up after bending forward
- Pins and needles, numbness or weakness in the leg or foot, which may suggest nerve involvement
Two timing patterns deserve their own line. Morning stiffness that eases within half an hour of moving is common and mechanical. Stiffness that regularly lasts more than an hour, particularly in younger adults, improving with exercise rather than rest, can suggest an inflammatory type of back pain and deserves a GP review. And night pain that repeatedly wakes you, does not change with position, or comes with feeling unwell, weight loss or fever should be assessed medically.
What Does Back Pain Feel Like?
Back pain feels different from person to person. Some describe a constant low-level ache, tightness or pressure. Others feel sudden sharp pain, catching, spasm, burning, or an electric-shock sensation with certain movements. If a nerve is irritated, symptoms may travel into the buttock, hamstring, calf or foot as shooting pain, pins and needles, numbness or weakness.
How the pain behaves is more useful than the word used to describe it. Mechanical pain changes with movement and position: easier walking, worse sitting or bending. Inflammatory-type pain tends to be worse at rest and at night, and better with movement.
Pain is also shaped by the nervous system. Two people can have similar scans and completely different pain, because stress, poor sleep, previous experiences and fear of movement all raise sensitivity. This does not mean the pain is imagined; it means pain is produced by the body and nervous system together, and both respond to treatment.
A useful step before any appointment: notice what makes your pain better and worse, whether it travels, how it changes through the day, and whether it affects sleep, work or walking. That behaviour is the most valuable information you can bring.
Clinical insight from One Body LDN
"The question we hear most in clinic is whether the pain means something is damaged. For most persistent back pain, the honest answer is that the back has become sensitised and deconditioned rather than injured. That changes the treatment completely: what a sensitised back needs is graded movement and rebuilt strength, which is usually the opposite of the protection people have been giving it."Rebecca Bossick — Chartered Physiotherapist & Clinical Director
How Long Does Back Pain Last?
Acute back pain, under six weeks, often improves within days to weeks with the right advice, gentle movement and self-management. Sub-acute pain, six to twelve weeks, usually needs a more structured rehabilitation plan. Persistent pain beyond twelve weeks benefits most from a combined approach: education, graded exercise, strength work, lifestyle changes and rebuilding confidence in movement.
Most simple episodes improve within a few weeks, particularly when you stay gently active and avoid prolonged bed rest. Pain lasting beyond that does not automatically mean something serious is wrong, but it does suggest your body needs a more structured plan than time alone.
Signs you are improving: better movement, less morning stiffness, fewer flare-ups, improved walking tolerance, better sleep, and a gradual return to normal activity. Signs you need more help: pain getting worse, travelling further down the leg, increasing numbness or weakness, or repeatedly stopping you working, training or sleeping.
When Does Back Pain Need Urgent Medical Attention?
- Loss of bladder or bowel control, or new difficulty passing urine
- Numbness or loss of sensation around the groin, genitals or saddle area
- Severe or rapidly worsening weakness in one or both legs
- Pain, tingling or numbness affecting both legs
- Back pain after significant trauma, such as a fall from height or road accident
- Chest pain alongside back pain
Seek urgent GP advice or call 111 if you have back pain with:
- Fever, chills or feeling generally unwell
- Unexplained weight loss
- A history of cancer with new back pain
- Constant pain that does not change with position or repeatedly wakes you
- Progressive numbness, pins and needles or weakness
How Is Back Pain Diagnosed?
Diagnosis starts with a detailed conversation: when the pain began, where you feel it, what changes it, whether symptoms travel, and whether any red flags need medical review first.
The assessment then typically includes observation of posture and walking, active movement testing, strength testing of the hips, legs and trunk, neurological testing where nerve involvement is suspected, and specific clinical tests for the discs, facet joints, sacroiliac joints and nerve roots where appropriate, finishing with functional testing built around your goals, whether that is sitting tolerance, lifting or running.
Imaging such as MRI or X-ray is not routinely needed for most non-specific back pain. Scans earn their place when serious pathology is suspected, symptoms are not improving as expected, or the result would genuinely change the plan.
Many people have disc bulges and age-related changes on scans without any pain, so images are always interpreted alongside your symptoms and examination. In most cases, careful clinical assessment is enough to begin safe, effective treatment.
How Is Back Pain Usually Treated?
- Self-management and education: understanding your pain, staying active, pacing, and knowing what to do in a flare-up
- Physiotherapy: assessment, advice, hands-on treatment where appropriate, exercise prescription and a clear recovery plan
- Exercise and rehabilitation: structured work on strength, flexibility, control and load tolerance
- Manual therapy: joint mobilisation and soft-tissue treatment used alongside exercise, not instead of it
- Medication: short-term anti-inflammatories help some people, though they are not a long-term answer, and paracetamol alone is not usually recommended for back pain
- Psychological approaches: education, reassurance and cognitive behavioural approaches help persistent pain, particularly where fear or avoidance has taken hold
- Injections and surgery: considered only in specific cases, such as severe nerve-related leg pain, where symptoms, examination and imaging all match and conservative care has not helped
Prolonged bed rest is not helpful for most back pain. Gentle activity, graded exercise and a structured plan produce better long-term results. For ongoing symptoms, our back pain physiotherapy in London team assesses within days through direct access, no referral needed.
Where Does Physiotherapy Fit Into Back Pain Care?
Physiotherapy helps when back pain is affecting movement, work, sleep or training, or when symptoms keep returning. The aim is not only short-term relief but understanding what is driving the problem and building a plan that restores confidence.
Your first appointment covers your history, work demands, training, sleep, stress and goals, then assessment of movement, strength and nerve function where needed. From there, your physiotherapist explains what is likely happening and outlines the plan: hands-on treatment where appropriate, movement advice, strength work, graded exposure to the movements you have been avoiding, and a progressive return to normal activity.
A good plan should leave you knowing what is safe, what to do in a flare-up, how to rebuild strength, and how to stop the same problem returning.
What Exercises and Rehab Help Back Pain?
Exercise is the most important long-term tool for managing and preventing back pain, and the right exercises depend on your symptoms, stage and goals.
Early on, gentle movement wins: short walks, comfortable position changes, and easy mobility work, reducing stiffness without forcing through pain.
As symptoms settle, rehabilitation becomes structured: trunk control work, glute and hip strengthening, mid-back mobility, and gradual loading through hinging, squatting and carrying patterns, progressing to return-to-sport or return-to-gym work for runners, lifters and athletes. The region-specific programmes, including the detail of what to do and when, sit in the lower back pain and upper back pain guides.
For persistent pain, the key principle is graded exposure: starting below your current tolerance and building gradually, which reduces sensitivity and rebuilds strength and confidence together.
Lifestyle habits matter alongside. Desk workers need regular movement breaks. People who train need to avoid sudden jumps in volume. Poor sleep slows recovery, and high stress amplifies pain. A complete plan considers all of it.
How Can You Reduce the Risk of Back Pain Coming Back? ?
Long-term recovery is about capacity: how much sitting, walking, lifting, training and daily life your back can tolerate without flaring. Reducing recurrence usually means improving strength in the muscles supporting the spine, hips and pelvis, mobility through the spine and hips, load tolerance built gradually, confidence in movement, and the recovery habits, sleep, pacing, desk setup and training progression, that flare-ups feed on.
The goal is not feeling better for a few days. It is understanding your back and reducing the risk of the same problem returning.
When Should You Get Help for Back Pain?
Frequently Asked Questions
What does back pain feel like?
Can back pain go away on its own?
When should I worry about back pain?
Can physiotherapy help back pain?
Yes. Physiotherapy assesses movement, strength, nerve function and daily triggers, then combines advice, hands-on treatment where appropriate, strengthening and a progressive return-to-activity plan.
What should I read next?
For region-specific depth, start with the lower back pain or upper back pain guide depending on where yours sits. For treatment, visit back pain physiotherapy in London.
What is the best sleeping position for back pain?
There is no single correct position, and comfort is the guide. Side-lying with a pillow between the knees, or lying on your back with a pillow under them, reduces strain for many people. Changing position through the night is normal and healthy; chasing one perfect posture usually backfires.
Should I use heat or ice on my back?
Either can help short-term, and neither repairs anything. Heat suits stiffness and muscle spasm; ice suits fresh flare-ups, in short spells. Use whichever eases symptoms enough to keep you moving, because the moving is the part that treats the problem.
Is my mattress causing my back pain?
Can I go to the gym or lift weights with back pain?
Is walking good for back pain?
Why does my back go into spasm, and is it dangerous?
Is cracking my back harmful, and why does it feel better?
Need Help With Ongoing Back Pain?
References
- National Institute for Health and Care Excellence (NICE). Low back pain and sciatica in over 16s: assessment and management (NG59).
- NHS. Back pain overview.
- Hartvigsen J, Hancock MJ, Kongsted A, et al. What low back pain is and why we need to pay attention. The Lancet. 2018.
- Hayden JA, Ellis J, Ogilvie R, et al. Exercise therapy for chronic low back pain. Cochrane Database of Systematic Reviews. 2021.
- Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR. 2015.
- Chartered Society of Physiotherapy. Low back pain

Medically reviewed by Rebecca Bossick, Lead Clinical Physiotherapist, HCPC & CSP Registered.
Last reviewed: May 2026