
Foot Pain: Symptoms, Causes, Treatment and When to See a Physio
Key Takeaways
- Where foot pain sits points to its cause: under the heel on first steps means plantar fasciitis, the ball of the foot means metatarsalgia or a nerve, and the back of the heel belongs to the achilles.
- Sharp heel pain on the first steps of the morning is the most reliable signature plantar fasciitis gives, and it is very treatable.
- Heel spurs on X-rays are usually bystanders: they appear on scans of pain-free feet, and treating the fascia resolves the pain with the spur still in place.
- Most foot pain is a load story, built from footwear, standing hours and training changes, which is why strengthening and load management fix it.
- Inability to take four steps after injury, a hot swollen foot with fever, or a non-healing sore, urgent with diabetes, need same-day medical review.
What is Foot Pain?
Where Does Your Foot Hurt? Location Points to the Cause
Under the heel
The arch and sole
Aching, burning, or stabbing pain through the arch or the bottom of the foot usually belongs to the plantar fascia or the small muscles of the sole, overloaded by standing, walking distance, or a training jump. Pain in the sole is the single most common foot complaint we see.
The back of the heel
The side of the foot
The top of the foot
Aching across the top, worse in laced shoes or when lifting the toes, points to the extensor tendons or the midfoot joints, common after distance increases and in tightly laced trainers.
The back of the heel
Main Types of Foot Pain
Plantar Fasciitis (Heel Pain)
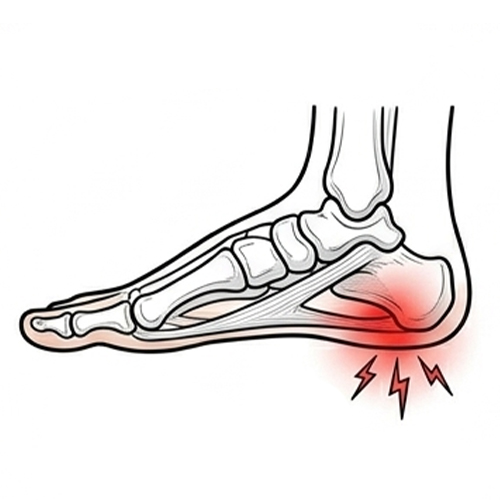
The most common cause of heel pain there is: irritation of the strong band of tissue running from heel to toes. The tell is the timing, sharp first steps in the morning or after rest, easing as you move, often returning after long days.
It affects one foot or both, and despite the pain it causes, it is very treatable: calf and foot strengthening, load management, and footwear changes carry the evidence, with shockwave therapy backed for stubborn cases. A note on heel spurs: they show up on scans of pain-free feet constantly and are rarely the cause of the pain, so a spur on an X-ray is not a life sentence.

Metatarsalgia (Ball of Foot Pain)

Achilles Tendinopathy

Post-Injury or Post-Surgical Foot Pain
Flat Feet and Over-Pronation Strain

Arthritis and Joint Changes

Nerve-Related Pain (Morton's Neuroma and Others)
Common Causes and Contributing Factors
- Overuse and repetitive impact: running, standing all day, long walking hours
- Poor or worn-out footwear, and sudden switches between shoe types
- Flat feet or high arches altering load distribution
- Weak calf and intrinsic foot muscles
- A tight calf and achilles complex, one of the most common drivers of heel pain
- Previous foot or ankle injury
- A sudden change in activity, distance, or surface
Symptoms and What They Mean
- Sharp or stabbing pain under the heel or arch, the fascia's signature
- Pain on the first steps in the morning or after rest that eases with movement
- Aching or burning along the ball or sides of the foot
- Pain mainly when bearing weight, standing, walking, or pushing off, which points to overloaded tissue doing its job under protest
- Swelling or tenderness around the toes or midfoot
- Tingling, numbness, or electric sensations into the toes, which bring the nerves in
- Reduced walking tolerance, or a limp you did not choose
Clinical insight from One Body LDN
""The structure we examine first in stubborn heel pain is not in the foot at all. A calf that has lost strength and length transfers its share of every step into the plantar fascia, and we rarely see a long-standing case without that deficit underneath it. It is why our plantar fasciitis rehabilitation is built around the calf as much as the sole, and why insoles alone so often disappoint."Rebecca Bossick — Chartered Physiotherapist & Clinical Director
How Long Does Foot Pain Last?
Acute foot pain, under six weeks, often improves quickly with load management, footwear adjustments, and targeted treatment. Sub-acute pain, six to twelve weeks, usually needs structured rehabilitation and progressive strengthening.
Persistent pain beyond twelve weeks benefits from gait retraining, load management, and strengthening to rebuild tissue capacity, and it stays treatable: plantar fasciitis in particular can run months when left alone, and responds much faster when treated properly than when waited out. Early treatment is the difference between a short episode and a long one.
When Foot Pains Needs Urgent Attention (Red Flags)
- Sudden severe pain, swelling, or deformity after injury, or inability to take four steps, which earns a fracture check the same day
- A hot, red, swollen foot or toe joint with fever or feeling unwell, which can signal infection or gout and needs same-day review
- Calf swelling, heat, and tenderness alongside foot symptoms, which can signal a clot
- Numbness, coldness, or colour change in the foot, suggesting circulation or nerve involvement
- Burning or numbness across both feet, which deserves a GP review for nerve causes
- A sore or wound on the foot that is not healing, urgent if you have diabetes
- Unexplained night pain or major swelling without injury
If you are unsure, your physiotherapist can triage all of these and refer for imaging or specialist review the same day where needed. After a heavy impact, our fracture treatment page covers that route.
How Physiotherapists Diagnose Foot Pain
- Take a thorough history of your symptoms, footwear, training, and activity patterns
- Assess alignment, mobility, and walking or running mechanics
- Test strength, flexibility, and balance through the foot, ankle, and calf
- Identify the contributors: tight calves, weak intrinsic foot muscles, load spikes
- Use focused clinical tests to separate fascia, tendon, joint, bone, and nerve
Physiotherapy Treatment for Foot Pain
Physiotherapy remains one of the most effective and evidence‑based solutions for foot pain. Treatment may include:
Hands‑On Physiotherapy
Exercise Therapy
Movement Retraining
Rehabilitation Programmes
How Physiotherapy Helps Long Term
Physiotherapy restores healthy foot mechanics, strengthens the muscles that support your arches, settles irritated tissue, improves walking and running efficiency, and teaches you the footwear and load habits that stop the next episode. Feet respond to strengthening as reliably as any body part, they are simply asked to work while they recover, which is exactly what a staged plan manages.
When to See a Physio
- Pain persists beyond two to three weeks or keeps returning
- Weight-bearing or walking is becoming difficult
- Morning heel or arch pain has become a daily fixture
- The pain is changing how you walk
- You are unsure which shoes, stretches, or activities are safe
Early treatment prevents minor strain from progressing into chronic pain, and a foot problem that has started altering your gait is already spreading its costs upward.
Take the Next Step Toward Recovery
Learn more about foot pain
Frequently Asked Questions
Does plantar fasciitis go away on its own?
Why does my foot hurt most on the first steps in the morning?
Can I keep walking or running with plantar fasciitis?
What are the best shoes or insoles for plantar fasciitis?
Why do the soles of both my feet hurt?
Can plantar fasciitis cause knee, hip, or back pain?
Should I use ice, and do the rolling exercises help?
Why does my heel or foot hurt more at night?
What is a heel spur, and do I need it removed?
Why does the top of my foot hurt?
My foot hurts only when I put weight on it. What does that mean?
Can physiotherapy really fix flat feet?
When should I see a physiotherapist rather than a podiatrist?
How do I get rid of foot pain fast?
References
- Morrissey D, Cotchett M, Said J'Bari A, et al. Management of plantar heel pain: a best practice guide informed by a systematic review, expert clinical reasoning and patient values. British Journal of Sports Medicine. 2021;55(19):1106-1118.
- Babatunde OO, Legha A, Littlewood C, et al. Comparative effectiveness of treatment options for plantar heel pain: a systematic review with network meta-analysis. British Journal of Sports Medicine. 2019;53(3):182-194.
- Rathleff MS, Mølgaard CM, Fredberg U, et al. High-load strength training improves outcome in patients with plantar fasciitis: a randomized controlled trial with 12-month follow-up. Scandinavian Journal of Medicine & Science in Sports. 2015;25(3):e292-e300.
- Moya D, Ramón S, Schaden W, Wang CJ, Guiloff L, Cheng JH. The role of extracorporeal shockwave treatment in musculoskeletal disorders. Journal of Bone and Joint Surgery. 2018;100(3):251-263.
- Kirkpatrick J, Yassaie O, Mirjalili SA. The plantar calcaneal spur: a review of anatomy, histology, etiology and key associations. Journal of Anatomy. 2017;230(6):743-751.
- NHS. Foot pain
- NHS. Diabetes: foot care.

This page has been reviewed for clinical accuracy, clarity and patient safety in line with One Body LDN's Editorial and Clinical Standards.