


Whiplash usually settles within two to three months. That is the NHS guidance, and it holds for most people. The problem is that “most” is not “all”. Around half of people still report some neck pain a year after the injury.
The difference between the two groups is rarely the crash itself. It is what happens in the first six weeks. This guide maps the three phases of whiplash recovery, what normal progress looks like in each, and the point at which self-care has done its job and physiotherapy should take over.
Key takeaways
- Whiplash is a mechanism of injury, not a single diagnosis. The neck is thrown forward and back faster than the muscles can brace.
- Most people improve within 2 to 3 months. Around 50% still report some neck pain at 12 months.
- Recovery runs in three phases: acute (0 to 6 weeks), recovery (6 to 12 weeks), and persistent (12 weeks and beyond).
- Early movement speeds recovery. A collar, prolonged rest, and fear of moving slow it down.
- Slow progress by week 3 to 4, or no progress by week 6, is the point to book a physiotherapy assessment rather than wait.
What whiplash does to the neck
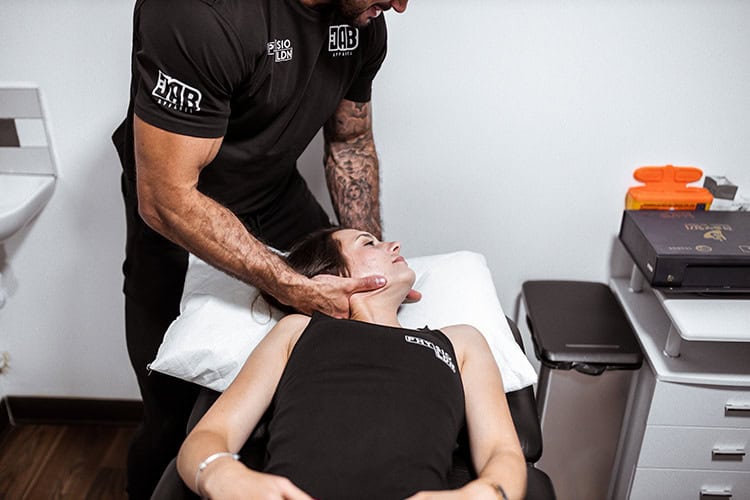
Whiplash is an acceleration-deceleration injury that strains the soft tissues of the cervical spine, most often after a rear-end collision.
The head lags behind the body as the car moves, then snaps forward. The muscles, ligaments, and small facet joints of the neck are loaded faster than they can protect themselves. The result is a sprain of those tissues. In most cases there is no fracture and no nerve damage.
Symptoms often start hours later, not at the scene. Stiffness, a dull ache across the back of the neck, headache at the base of the skull, and pain turning the head are the usual pattern. Some people also notice dizziness, tiredness, or trouble concentrating in the first fortnight.
Whiplash sits inside the broader category of neck pain, but its cause is traumatic rather than postural or degenerative. That matters for the timeline. A traumatic sprain heals on a known schedule. Postural neck pain does not.
The WAD grading system
Clinicians grade whiplash using the Quebec Task Force scale for whiplash-associated disorders (WAD):
- Grade 0: no neck symptoms and no physical signs.
- Grade I: neck pain, stiffness, or tenderness only. No physical signs on examination.
- Grade II: neck symptoms plus physical signs such as reduced range of motion or tender points.
- Grade III: neck symptoms plus neurological signs such as weakness, altered reflexes, or sensory loss.
- Grade IV: neck symptoms with a fracture or dislocation.
Most people seen in physiotherapy are Grade I or II. Grade III needs medical assessment before rehabilitation. If arm symptoms are the main feature, the pattern is closer to cervical radiculopathy and is assessed differently. Grade IV is an emergency.
The three phases of whiplash recovery
Whiplash recovery follows a predictable phase pattern. Most people move through all three in under 12 weeks.
Phase 1: Acute (0 to 6 weeks)
The first 72 hours are the most painful. Inflammation peaks, muscles guard, and turning the head feels unsafe. This is normal and does not mean serious damage.
Progress in this phase is measured by movement, not by pain. By the end of week 1, you should be able to turn your head further than on day 2. By week 3, everyday tasks such as driving, checking a blind spot, and looking up should be uncomfortable rather than impossible.
NHS advice for this phase is clear. Take paracetamol or ibuprofen. Keep doing everyday activities even if they hurt a little. Do not use a neck collar. Do not rest the neck for long periods. Early movement is the single most important factor in a short recovery.
Phase 2: Recovery (6 to 12 weeks)
Pain drops to a background ache. Range of motion returns to near normal. The remaining work is strength and endurance. The deep neck flexors and the muscles between the shoulder blades are often weak after weeks of guarding, and that weakness is what causes the late-afternoon ache and the headache that returns after a day at a screen.
Most people are back to full work and sport by the end of this phase. The NHS figure of 2 to 3 months lands here.
Phase 3: Persistent (12 weeks and beyond)
Symptoms that continue past 12 weeks are classed as persistent or chronic whiplash. This group is larger than most people expect. The Bone and Joint Decade Task Force review found that around 50% of people with WAD still report neck pain one year after injury. For many it is mild. For a smaller group it limits work and sleep.
Persistent whiplash is not a sign that the original injury was worse. It is usually a sign that movement, strength, and confidence did not return on schedule.
What makes whiplash recovery slower

The strongest predictors of slow whiplash recovery are high early pain, early disability, and avoiding movement, not the severity of the collision.
Research across whiplash cohorts points to the same factors again and again:
- High pain intensity in the first week. Severe early pain is the most consistent predictor of symptoms at 6 and 12 months.
- Reduced neck movement straight after injury. Stiffness that is not addressed early tends to persist.
- Fear of movement. Protecting the neck feels sensible. It delays recovery.
- Passive coping. Waiting for the pain to go rather than working through graded movement.
- Low mood and poor sleep in the first weeks.
- Older age and a previous neck injury.
Crash factors such as impact direction, speed, and headrest type are rarely prognostic. Two people in the same car can have very different recoveries.
The practical point is that almost every factor on that list can be changed in the first six weeks. That is why early physiotherapy makes a difference for people whose progress stalls.
When self-care is no longer enough
Self-care should produce visible progress by week 3. If it has not, or if progress stops before week 6, physiotherapy should take over.
Use these checkpoints:
- Day 7: no improvement at all. NHS advice is to see a GP. A physiotherapy assessment at this point is also appropriate.
- Week 3 to 4: still unable to check a blind spot, look up, or work a full day. Progress is behind schedule.
- Week 6: pain is the same as week 2, or movement is still restricted. Self-care has done what it can.
- Any point: a headache that is getting worse, dizziness that persists, or new arm symptoms.
Whiplash physiotherapy at this stage focuses on restoring range of motion, retraining the deep neck muscles, graded exposure to the movements you have been avoiding, and a clear plan for returning to driving, work, and sport. Our private whiplash physiotherapy in London is built around that progression. Most people who start treatment in the recovery phase do not go on to develop persistent symptoms.
If you are already past 12 weeks, treatment still works. The programme is longer and includes more strength and endurance work, but whiplash recovery support at the persistent stage still changes outcomes.
Frequently asked questions
How long does whiplash take to heal completely?
Most whiplash settles within 2 to 3 months. Around half of people still report some neck pain at 12 months, so full recovery for a minority takes longer. The soft tissue heals well within 6 to 12 weeks. Ongoing symptoms after that point are usually driven by stiffness, weakness, and movement avoidance rather than unhealed tissue.
Can whiplash symptoms appear days after the accident?
Yes. Whiplash symptoms often start 6 to 24 hours after the collision and can take two to three days to peak. Adrenaline at the scene masks early pain. Delayed onset does not mean the injury is worse.
Should I wear a neck collar for whiplash?
No. The NHS advises against neck braces or collars for whiplash because they slow recovery. A collar stops the movement that the neck needs to heal. Gentle, regular movement from day one is the better option.
Is it normal for whiplash to get worse before it gets better?
Yes, in the first 72 hours. Pain and stiffness usually peak on day 2 or 3, then start to ease. Worsening after the first week is not the normal pattern and needs assessment.
When should I see a physio for whiplash?
Book a physiotherapy assessment if there is no improvement by day 7, if progress is behind schedule at week 3 to 4, or if symptoms plateau by week 6. Earlier is better. The factors that predict persistent whiplash are all easier to change in the first six weeks.
Book your whiplash assessment
Whiplash heals on a schedule. If your recovery is behind that schedule, waiting rarely fixes it. The One Body LDN whiplash team assesses acute, recovering, and persistent whiplash across our London clinics, with same-week availability and no GP referral needed. You can also see our wider neck pain physiotherapy in London if your symptoms have changed since the injury.
Note: whiplash symptoms that need urgent medical care
Contact NHS 111 or ask for an urgent GP appointment if you have any of the following after a neck injury:
- Severe pain that paracetamol or ibuprofen does not touch
- Tingling or pins and needles on one or both sides of the body
- Weakness in the hands, arms, or legs
- A sudden electric-shock sensation in the neck or back
- Difficulty walking or sitting upright
Do not drive or cycle until you have spoken to a GP or NHS 111. Call 999 if symptoms came on immediately after a high-speed collision and you cannot move your neck at all.
References
- NHS. Whiplash.
- Carroll LJ, Holm LW, Hogg-Johnson S, et al. Course and prognostic factors for neck pain in whiplash-associated disorders (WAD). Bone and Joint Decade 2000-2010 Task Force on Neck Pain and Its Associated Disorders.
- Institute for Work & Health. Summary: Course and prognostic factors for neck pain in whiplash-associated disorders.
- Spitzer WO, Skovron ML, Salmi LR, et al. Scientific monograph of the Quebec Task Force on Whiplash-Associated Disorders: redefining “whiplash” and its management. Spine 1995;20(8 Suppl):1S-73S.
- Bekkering GE, et al. KNGF Guidelines for Physical Therapy in Patients with Whiplash. Royal Dutch Society for Physical Therapy, 2003.
