
Elbow Pain: Symptoms, Causes, Treatment and When to See a Physio
Key Takeaways
- The side of the elbow that hurts usually names the condition: outer means tennis elbow, inner means golfer's elbow, inner with tingling fingers means the ulnar nerve, and the back points to bursitis or the triceps.
- Most elbow pain is tendon overload from gripping, lifting and typing, and rest alone fails it: rested tendons lose capacity rather than regain it.
- Tingling or numbness in the ring and little fingers points to a nerve rather than a tendon, and changes the treatment plan.
- Progressive loading of the forearm and grip is the best-evidenced treatment for tennis and golfer's elbow, with honest timescales running months for long-standing cases.
- A hot, red, swollen elbow with fever needs same-day medical care, as does an elbow that cannot bend or straighten after an injury.
What is Elbow Pain?
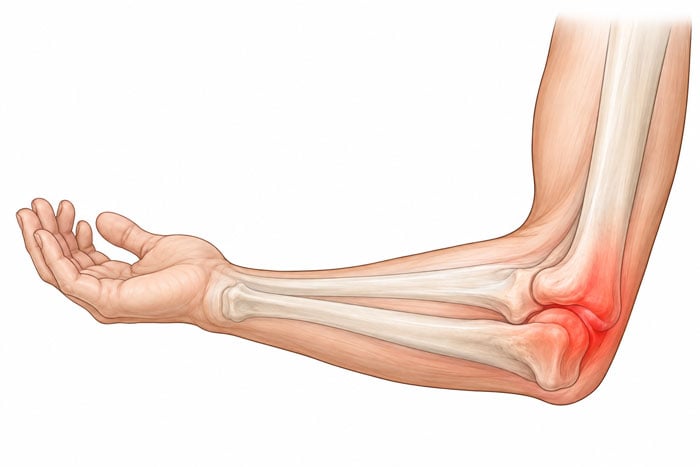
Elbow pain refers to discomfort or stiffness felt around the elbow joint or forearm. It can stem from tendon overload, joint stiffness, nerve sensitivity, or referred pain from the neck or shoulder. The elbow’s two bony points, one on the outer side, one on the inner, are the anchors for the muscle groups that power the grip and the wrist, and each complains at its own address when overloaded. An assessment works out which structure is involved, joint, tendon, or nerve, and builds a plan to restore strength, mobility, and pain-free function.
Main Types of Elbow Pain
Each condition has different triggers and recovery strategies — making professional diagnosis essential for lasting results.
Pain on the Outside
Pain at the Front
Referred Pain from the Neck or Shoulder
Pain at the Back
Pain on the Inside with Tingling Fingers:
Deep, Stiff, or Locking Elbow Pain
Pain on the Inside: Golfer's Elbow (Medial Epicondylitis)
Post-Injury or Post-Surgical Elbow Pain
Common Causes and Contributing Factors
- Repetitive gripping, typing, or lifting, the slow-build overloads
- A sudden increase in training, DIY, or manual load
- Poor wrist or shoulder mechanics pushing extra work through the elbow
- Muscle imbalance or forearm tightness
- Weak stabilising muscles at the wrist and shoulder
- Leaning habits and sustained pressure on the elbow point
In most cases elbow pain develops gradually from repetitive overload rather than a single injury, and the tendon deceives on the way: it often eases during activity and complains afterwards, which keeps people loading it until it escalates. Where the problem is tendon-driven, our tendonitis treatment page covers that pathway.
Symptoms and What They Mean
- Dull aching or sharp pain around the elbow joint
- Pain radiating into the forearm or wrist, the tendon pattern, which travels down the muscle rather than in a nerve line
- Weak or painful grip, difficulty lifting a kettle, a chair, or a bag
- Tenderness you can press on the inner or outer bony point
- Stiffness after inactivity or in the morning, and any loss of full straightening, which points into the joint
- Tingling or numbness in the fingers, which points to a nerve, at the elbow or the neck, and changes the plan
- Clicking, or swelling at the back of the joint
Clinical insight from One Body LDN
"The number we track most closely with elbow tendon pain is grip strength, measured against the other arm. Pain scores swing with good and bad weeks, but a grip that is steadily closing the gap tells us the tendon is genuinely rebuilding, and it usually improves before the pain fully leaves. That order is normal, and knowing it stops people abandoning a programme that is working."Rebecca Bossick — Chartered Physiotherapist & Clinical Director
How Long Does Elbow Pain Last?
Persistent pain beyond twelve weeks benefits from combined hands-on treatment and progressive exercise to rebuild resilience and reduce sensitivity, and elbow tendons reward that work reliably, though honest timescales for a long-standing tennis elbow run months, not weeks. Rest alone fails elbow tendons for a simple reason: rested tendons lose capacity rather than regain it. The sooner structured treatment begins, the easier the recovery.
When Elbow Pain Needs Urgent Attention (Red Flags)
- Sudden elbow deformity or severe swelling after trauma
- Inability to move, bend, or straighten the joint after an injury
- A hot, red, swollen elbow with fever or feeling unwell, which can signal an infected bursa or joint and needs same-day care
- Numbness or tingling in the fingers or forearm that is progressing, or hand weakness getting worse week on week
- An arm turning cold, pale, or numb
- Unexplained night pain, a lump, or rapid swelling without injury
If you are unsure, your physiotherapist can assess, screen for every one of these, and refer to the right medical professional the same day where needed.
How Physiotherapists Diagnose Elbow Pain
- Take a full history of your symptoms, work, training, and activity levels
- Test grip strength, wrist and elbow movement, and muscle control
- Press and load the specific tendon anchors to reproduce and locate the pain
- Assess the neck and shoulder's contribution, since referred pain wears an elbow disguise
- Identify whether symptoms involve tendons, the joint, or nerves, with specific clinical tests to confirm
Physiotherapy Treatment for Elbow Pain
Hands‑On Physiotherapy
Exercise Therapy
Movement Retraining
Rehabilitation Programmes
How Physiotherapy Helps Long Term
When to See a Physio
- Pain lasts more than two to three weeks or keeps recurring
- You struggle to grip, lift, or type without pain
- Tingling or numbness has joined the pain
- Swelling or stiffness is limiting daily tasks
- The pain returns with every spell of activity
Take the Next Step Toward Recovery
Learn more about elbow pain
Frequently Asked Questions
Should I use ice or heat on a painful elbow?
Do tennis elbow straps or braces work?
Should I get a steroid injection for tennis elbow?
Can I keep training at the gym with elbow pain?
Does massage help tennis or golfer's elbow?
How do I stop my fingers tingling at night?
I hit my funny bone and it still tingles. Should I worry?
Should I stretch or strengthen a painful elbow?
Why do both my elbows hurt?
What desk or mouse changes help elbow pain?
Why does my elbow click or crack?
My grip is weak but my elbow barely hurts. What does that mean?
References
- Coombes BK, Bisset L, Brooks P, Khan A, Vicenzino B. Effect of corticosteroid injection, physiotherapy, or both on clinical outcomes in patients with unilateral lateral epicondylalgia: a randomized controlled trial. JAMA. 2013;309(5):461-469.
- Bisset LM, Vicenzino B. Physiotherapy management of lateral epicondylalgia. Journal of Physiotherapy. 2015;61(4):174-181.
- Chen Z, Baker NA. Effectiveness of eccentric strengthening in the treatment of lateral elbow tendinopathy: a systematic review with meta-analysis. Journal of Hand Therapy. 2021;34(1):18-28.
- Yao G, Chen J, Duan Y, Chen X. Efficacy of extracorporeal shock wave therapy for lateral epicondylitis: a systematic review and meta-analysis. BioMed Research International. 2020;2020:2064781.
- Andrews K, Rowland A, Pranjal A, Ebraheim N. Cubital tunnel syndrome: anatomy, clinical presentation, and management. Journal of Orthopaedics. 2018;15(3):832-836.
- National Institute for Health and Care Excellence. Clinical Knowledge Summary: Tennis elbow.
- NHS. Tennis elbow.

This page has been reviewed for clinical accuracy, clarity and patient safety in line with One Body LDN's Editorial and Clinical Standards.